


Brian Blase, Ph.D., is the President of Paragon Health Institute. Brian was Special Assistant to the President for Economic Policy at the White House’s National Economic Council (NEC) from 2017-2019, where he coordinated the development and execution of numerous health policies and advised the President, NEC director, and senior officials. After leaving the White House, Brian founded Blase Policy Strategies and served as its CEO.
What The New York Times Gets Wrong About Obamacare

In an August 15 editorial, The New York Times offered a revisionist history of the Affordable Care Act (ACA) and badly mischaracterized recent actions by congressional Republicans and the Trump administration. Two telltale signs of a misleading ACA analysis are that it fails to explain just how heavily subsidized the individual market has become and that it ignores the widespread growth of improper and phantom enrollees in the ACA exchanges and Medicaid expansion. The Times editorial fails to mention either of these key facts—and contains a host of additional errors.
Let’s take a closer look.
Overstated Coverage Gains Came at a High Cost
The piece starts with “One of the federal government’s great achievements this century was making health insurance affordable to millions more Americans. In 2010, nearly 18 percent of people under 65 lacked insurance. By 2024, the rate had fallen below 10 percent, thanks to the Affordable Care Act and later legislation that built on it.” There are several problems with this.
First, the ACA did not make health insurance less expensive. Its insurance rules significantly increased premiums in the individual market and to a lesser extent those in the small group market.
Second, subsidies do not make health care less expensive; they simply shift costs from enrollees to taxpayers while weakening incentives to restrain premiums. Because taxpayers bear almost all the cost of premium increases for heavily subsidized enrollees, insurers face less pressure to keep premiums down. Taxpayers now pay more than 80 percent of premiums in the ACA exchanges.
Third, while the ACA did increase the number of people with coverage, much of that increase came through a massive expansion of Medicaid to able-bodied, working-age adults. The exchanges, which were supposed to create a robust and competitive individual insurance market, have badly underperformed expectations, with enrollment heavily dependent on federal subsidies and consumers often left with expensive, narrow-network plans.
Fourth, particularly during the Biden administration, lax eligibility verification and an ‘enroll first, ask questions second’ approach resulted in more than 10 million ineligible enrollees in ACA exchange plans and Medicaid expansion each year. Many of these enrollees were unaware that they had been signed up, had other coverage, or were fictional.
These phantom enrollees showed up in enrollment statistics but received no benefit from being in the ACA—although health insurers received large subsidies and brokers received large commissions because of that enrollment. The problem was perpetuated through automatic reenrollment, which allowed millions of people to remain in exchange plans without actively choosing coverage for the coming year.
The Real Story Behind the 2026 Enrollment Decline
The Times blames President Trump and congressional Republicans for a coverage decline, writing “They have effectively cut subsidies for the Affordable Care Act’s marketplaces, making it harder for people who do not receive insurance through work to afford a plan. This year, the subsidy cuts led three million people to lose their health insurance.”
This claim warrants multiple Pinocchios. In 2021, as a temporary COVID measure, a Democratic Congress significantly expanded the ACA subsidies. Congress explicitly scheduled those temporary subsidies to expire after 2025. Allowing a temporary subsidy—created to help people during the pandemic—to expire is not a “cut” enacted by Republicans.
The expanded subsidies increased enrollment, but they also dramatically increased federal costs and made fraud much more lucrative. By 2025, more than a quarter of exchange enrollees were likely improperly enrolled. In 2024, 35 percent of enrollees did not use their health plan a single time—double the rate expected in a normal health insurance market. And exchange enrollment remains more than 80 percent higher than pre-COVID levels.
Taxpayers Bear the Cost of Rising ACA Premiums
The underlying ACA subsidies rise on autopilot from one year to the next. The core feature of the subsidy construct is that the enrollee share of the premium is capped at a certain amount, meaning premium increases are picked up by taxpayers in the form of larger subsidies. The figure below illustrates this phenomenon for a fairly typical ACA enrollee—a 50-year-old earning twice the federal poverty level (FPL). Between 2014 and 2026, premiums increased by $5,898. But the enrollee share of that premium increase was only $618, as taxpayers have picked up $5,279—or 90 percent of the increase.

The ACA premium subsidies also create a major inequity between workers who receive coverage through an employer and people who purchase coverage through the exchanges. John R. Graham and I illustrated this inequity in a paper last year. For a family with two 35-year-old parents, two children, and income twice the FPL, the original ACA subsidy is more than three times as large as the tax benefit for job-based coverage. The COVID subsidy boosts widened the gap even further. The result is a system that treats similarly situated families very differently depending on where they obtain insurance, penalizes workers with job-based coverage, and gives employers a growing incentive to stop offering health benefits.
The Times is also wrong to attribute this year’s enrollment decline to people losing coverage because of the expiration of the COVID subsidy boosts. The expiration of those enhanced subsidies, combined with Trump administration program integrity efforts, is appropriately removing improper and phantom enrollees from the program. A June report from the Assistant Secretary for Planning and Evaluation at the Department of Health and Human Services (HHS) estimated that the entire net decline in effectuated enrollment from 2025 to 2026 was attributable to a reduction in improper and phantom enrollment.
The Times does acknowledge that Democrats “set [the COVID subsidy boosts] to expire in 2025, which mitigated their impact on the federal debt.” Making the temporary subsidies permanent would have cost roughly $40 billion a year over the next decade. With federal debt already at historically high levels, Congress was right not to make a temporary pandemic policy permanent. The underlying subsidies are projected to cost $117 billion this year, and as discussed above, the average subsidy is much larger than the tax benefit that people with employer coverage receive.
Which ACA Enrollees Face an Affordability Problem?
The people who do face a genuine affordability problem after the expiration of the temporary COVID subsidy boosts are those with incomes just above four times the FPL, the income level at which the ACA’s original subsidy structure capped assistance. These individuals now face the full cost of expensive ACA-regulated coverage, experiencing the exact same subsidy cliff that Democrats established in 2010 but with premiums inflated by over a decade of ACA’s regulations pushing up premiums. Senator Ron Johnson, among other Republicans, was focused on a targeted policy solution for those enrollees last fall, but he could not find enough support from congressional Democrats. Still, this is a relatively small group: only about 6 percent of all ACA enrollees report income above four times the FPL.
Medicaid Spending Is Still Rising
The Times next turns to the so-called “sweeping cuts to Medicaid.” But reducing the growth of projected spending is not the same as cutting actual spending. Even after the One Big Beautiful Bill (OBBB) reforms, the Congressional Budget Office (CBO) projects federal Medicaid spending will rise every year over the next decade. Spending in the first three quarters of this fiscal year is already up 10 percent from last year’s level. Remarkably, CBO now projects that federal Medicaid spending in 2035 will exceed what it projected at the start of the Biden administration—with a projected annual growth rate of about 3 percent.
What The Times leaves out is the extraordinary growth in both improper enrollment in the ACA Medicaid expansion and state financing schemes designed to maximize federal Medicaid payments. Some reforms—such as targeting the abuse of provider taxes—are less sweeping than what then-President Obama proposed and then-Vice President Biden publicly supported. State-directed payments have become a massive source of corporate welfare for hospitals and other providers. The Medicaid reforms in the OBBB begin to address both problems and shift a portion of the financing costs back to states, which have shifted so much of Medicaid’s cost to the federal government over the past 15 years. Fortunately for people with commercial coverage, HHS projects that the reforms to provider taxes and state-directed payments will also reduce commercial prices and premiums.
The Medicaid Expansion’s Broken Incentives
The Times is not a fan of the work/community engagement requirement in the OBBB, calling it “a paperwork requirement—one that forces Medicaid enrollees, most of whom are working or have a valid reason for not working, to file repeated documents proving they have a job or a valid exemption.” The Times does not mention that the work/community engagement requirement only applies to the able-bodied, working-age enrollees added to Medicaid by the ACA. For these enrollees, states receive seven times more federal funding for every $1 of their spending than they receive for traditional enrollees. That enormous funding disparity gives states a powerful incentive to maximize expansion enrollment and comparatively little incentive to police eligibility. As a new research paper by Liam Sigaud demonstrates, nearly half of Medicaid expansion enrollees appear to be ineligible for the program. Health insurance companies are receiving Medicaid payments on behalf of millions of enrollees who may not even be aware of their coverage.
Did Obamacare Really Control Health Care Costs?
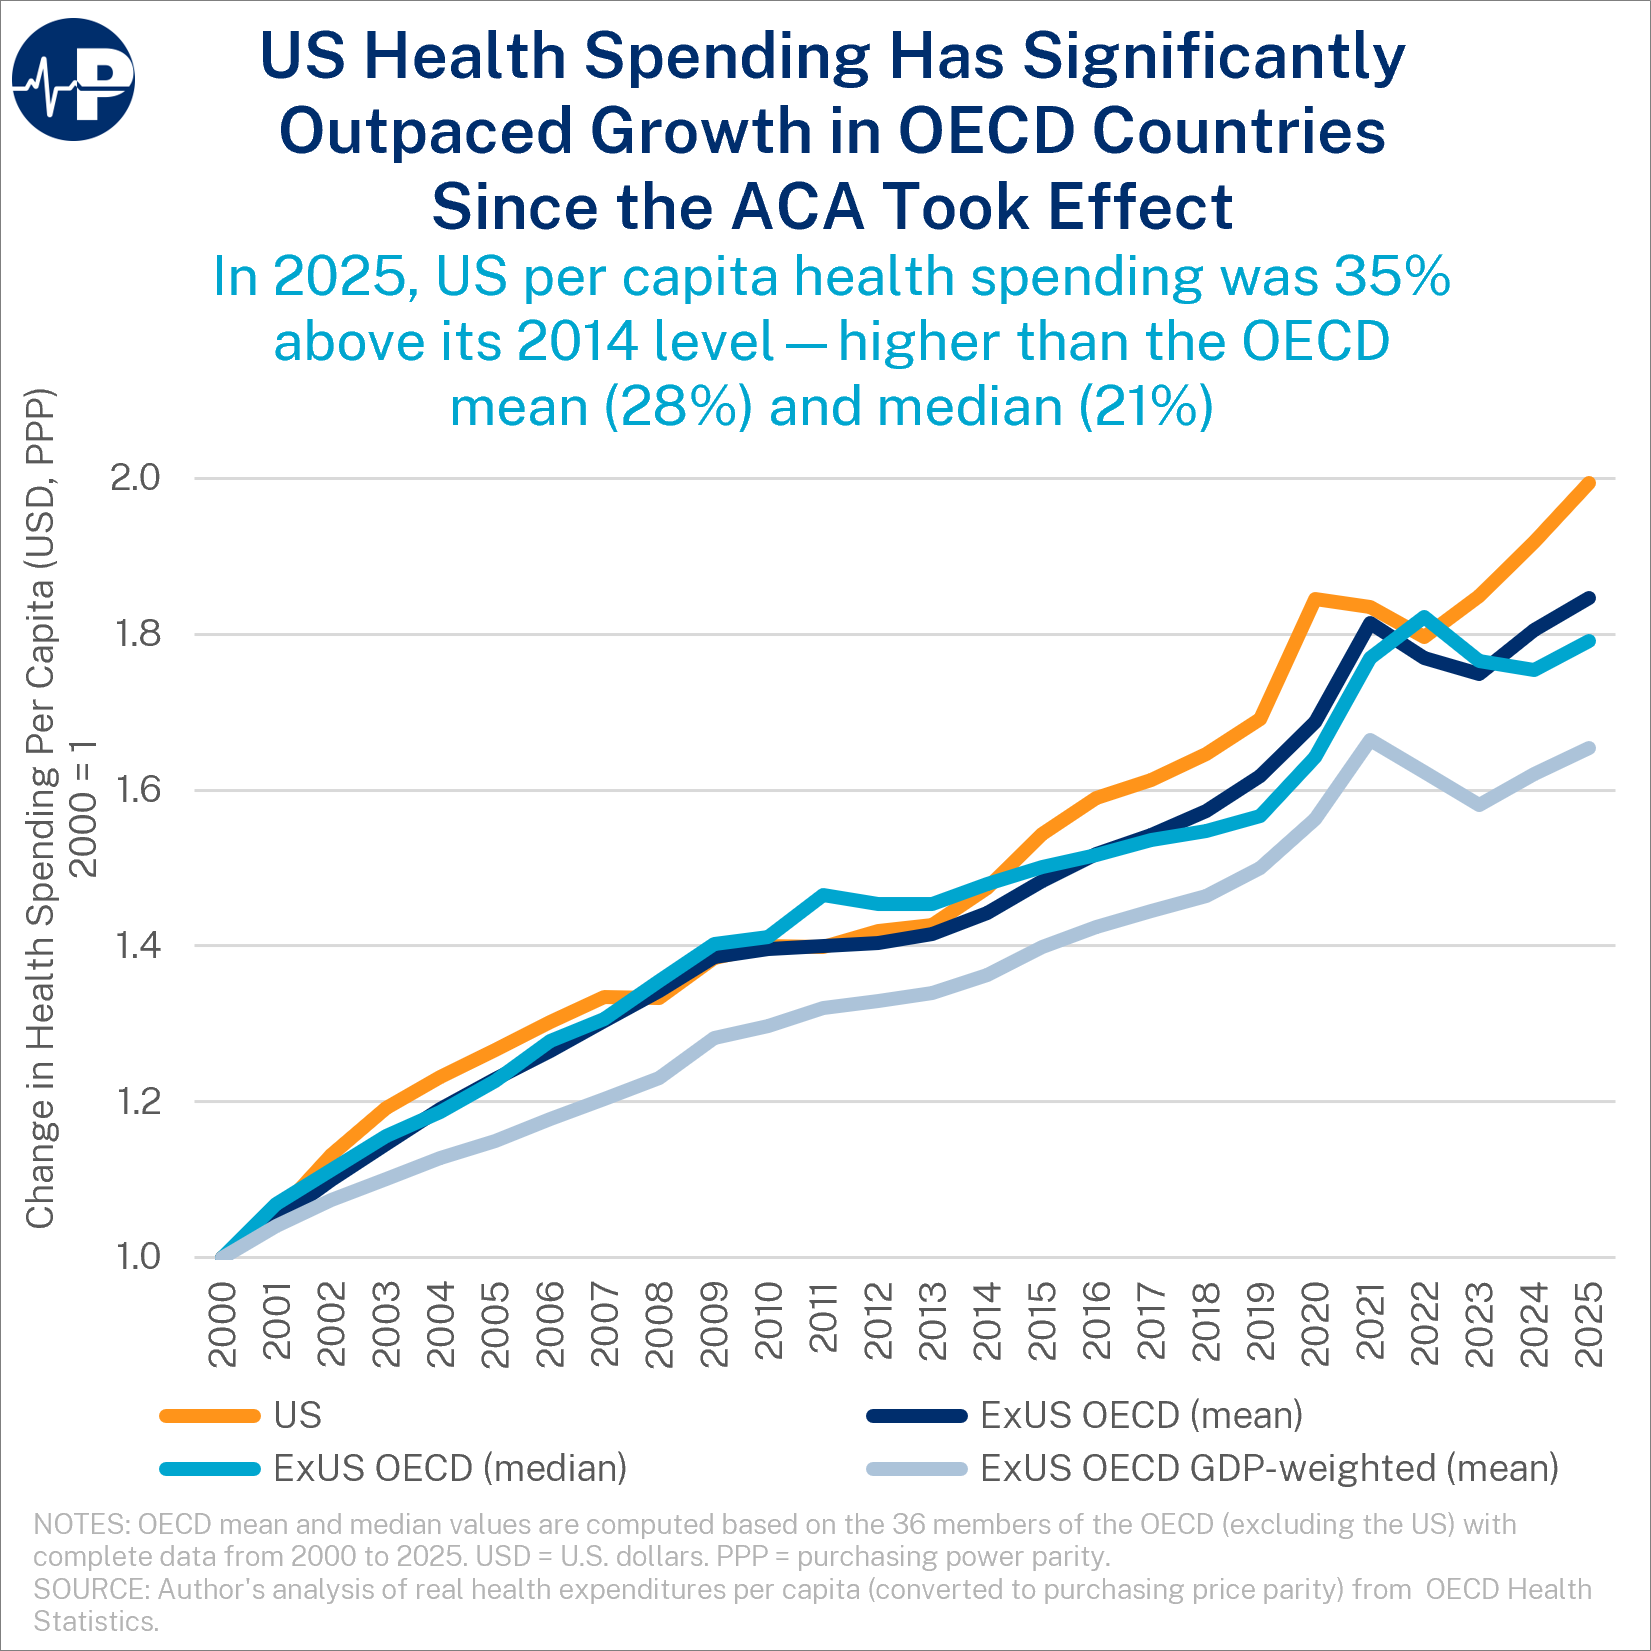
The Times goes on to say that “The Affordable Care Act also happens to be a model on costs; it meaningfully slowed growth in health care prices over the past decade.” First, the ACA does deserve some credit for slowing Medicare costs. In fact, the best feature of the ACA was likely the Medicare payment reductions. However, key components of the ACA led to escalating costs elsewhere. Individual market premiums, which were much more affected by the ACA than group premiums, have increased twice as fast as group premiums since 2014. There was a broader effect too as the ACA increased regulatory complexity and accelerated consolidation throughout the health sector, reducing competition and contributing to higher prices.
There was a slowdown in health care spending growth beginning around 2007, well before the ACA took effect, with the 2007–2009 financial crisis and the extremely weak recovery that followed playing a major role. Moreover, the slowdown was not unique to the United States. Health care spending growth slowed across advanced economies following the global financial crisis, strong evidence that broader economic forces—not the ACA—were a major cause of the slowdown.
The ACA’s Failure
The Times’ defense of the ACA ignores how far the law has fallen short of what its supporters promised. President Obama promised lower costs, more competition, and help for small businesses providing coverage. The ACA deserves some credit for reducing Medicare’s expenditure trajectory, but 15 years later, its overall record bears little resemblance to those promises. Rather than lowering costs and creating a robust and competitive individual market, the law produced a massive Medicaid expansion rife with abuse and an individual market characterized by high premiums, narrow networks, widespread improper enrollment, and enormous federal subsidies needed to make expensive coverage appear affordable. Far fewer small employers offer health insurance than before the ACA, while the law has significantly increased federal deficits.
Related Content

Subscribe
Sign up now for your health policy updates.