Figure 3 does not imply that improper enrollees come exclusively from the 18-to-64-year-old population below 150 percent of FPL. In fact, large numbers of improper enrollees in both Medicaid expansion and the exchanges are likely above 150 percent of FPL and understate their income in order to gain greater federal subsidies. As we have previously discussed, insurers and brokers have significant incentives for applicants to misstate income as insurers prefer premiums to be fully paid by taxpayers and brokers earn greater commissions when enrollment is higher.
Oregon Is an Outlier in Improper ACA Enrollment
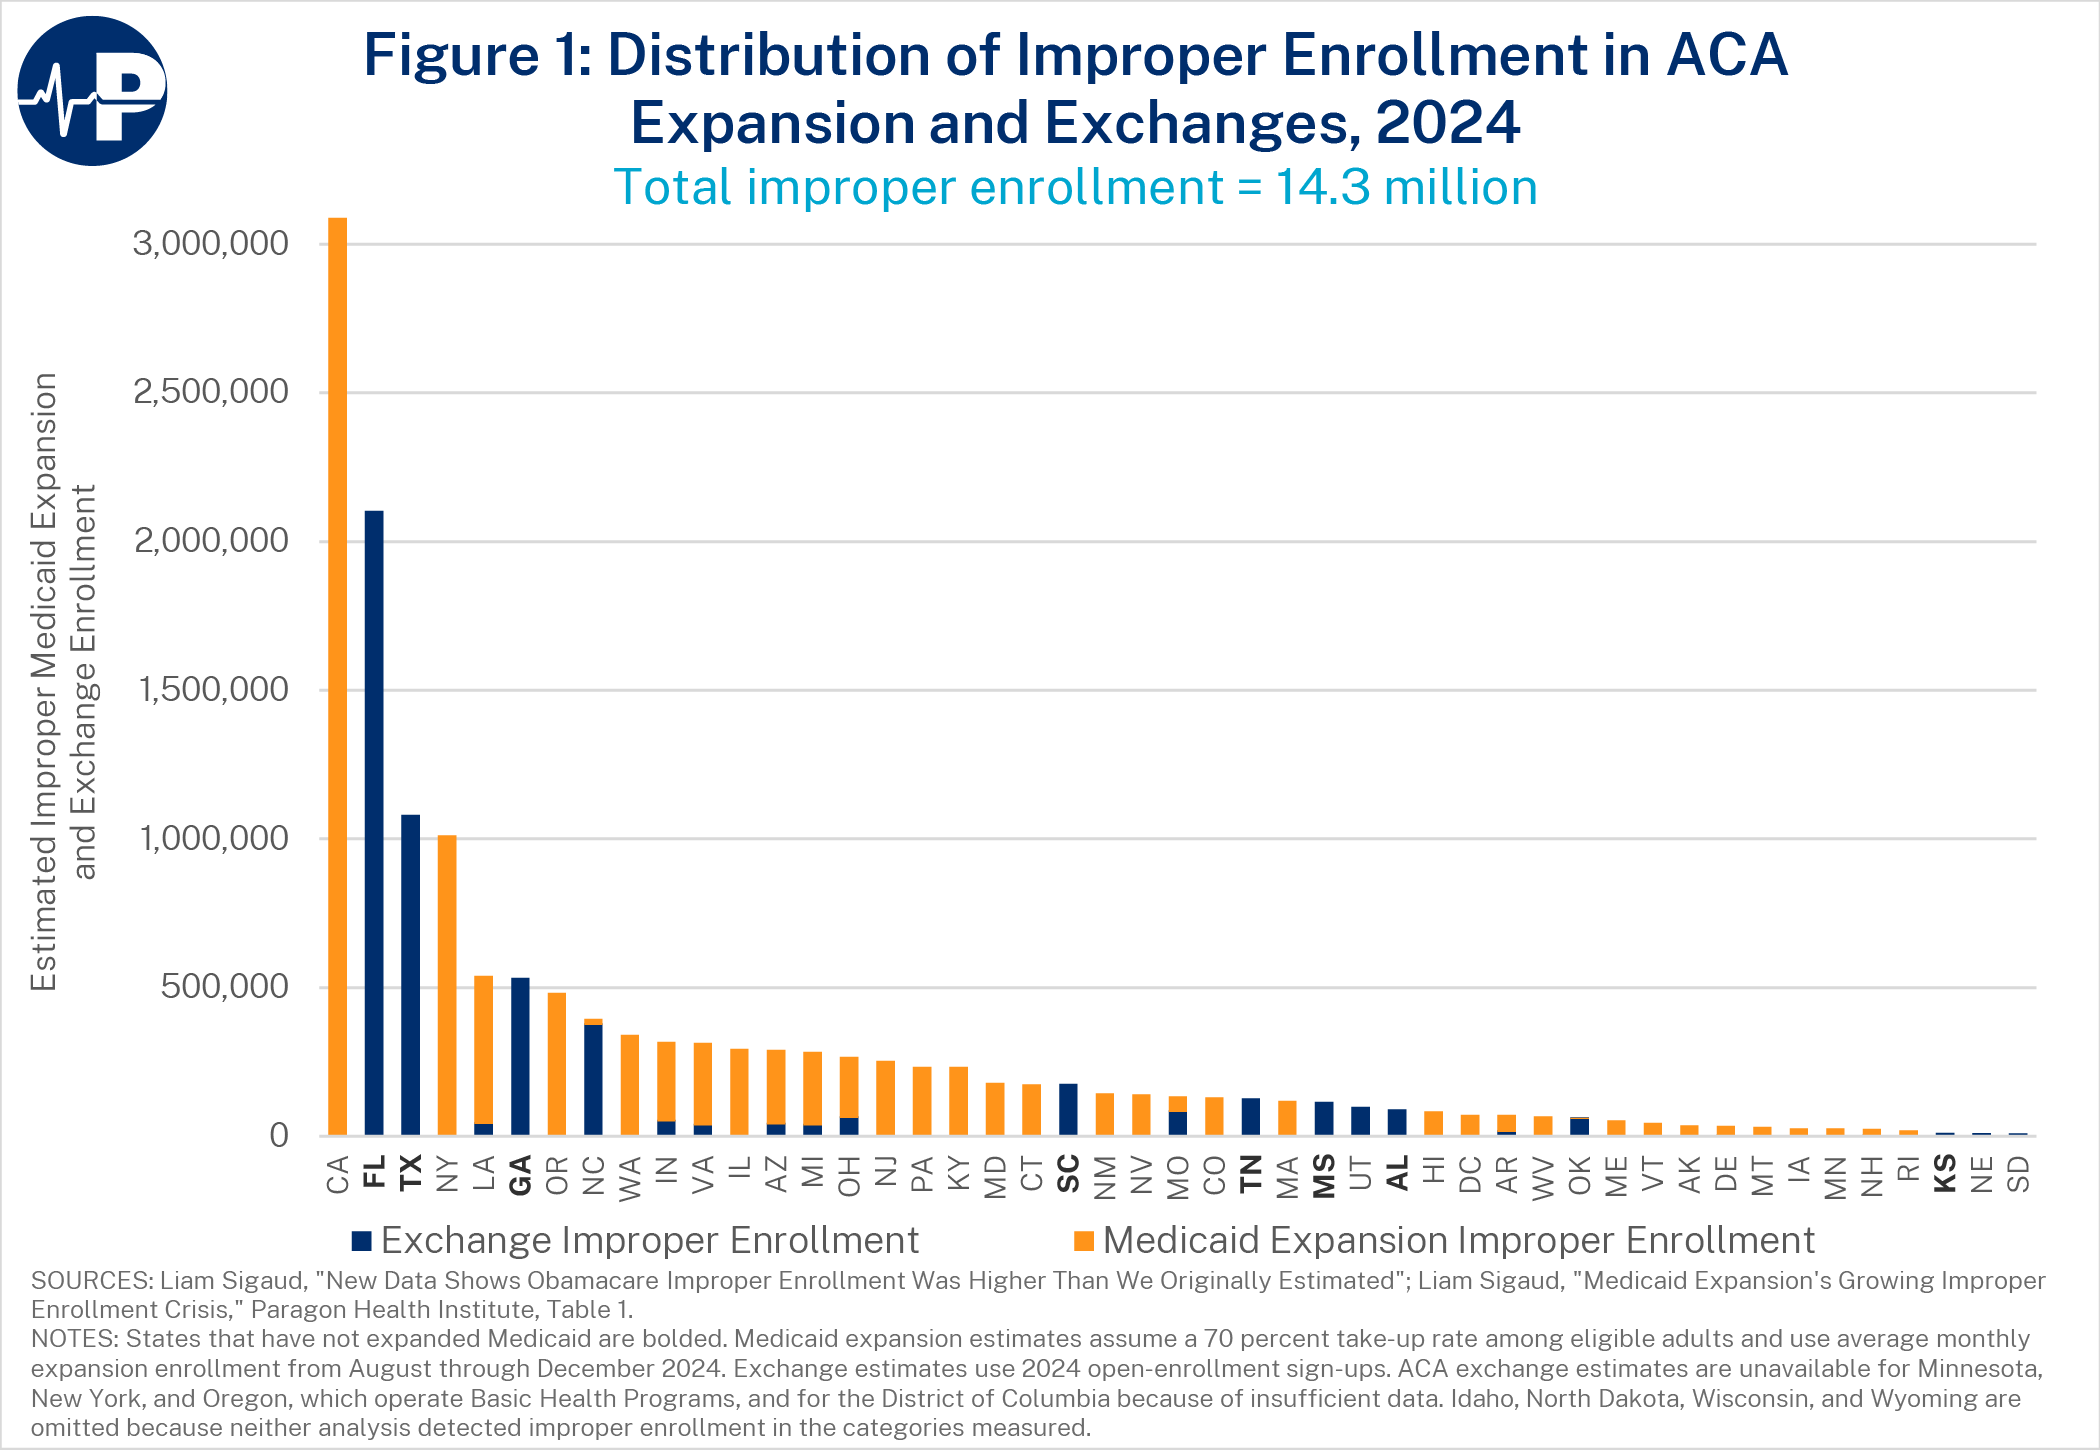
We estimate that more people are improperly enrolled in Medicaid expansion in Oregon than there are 18-to-64-year-olds below 150 percent of FPL in the state. As a point of comparison, Oklahoma—another expansion state with an overall population very similar to Oregon—had barely one-third the number of Medicaid expansion enrollees in 2024: 235,832 in Oklahoma vs. 662,695 in Oregon. This difference is especially stark given that Oklahoma has a higher poverty rate and lower median household income than Oregon, meaning a larger share of its population qualifies for Medicaid expansion.
Oregon’s unique policies may explain part of this result. Since July 2023, a Section 1115 waiver has permitted Oregon to provide most adults with 24 months of continuous Medicaid eligibility, allowing people to remain enrolled even if their incomes rise above the eligibility threshold. Another potential factor is that Oregon conducted final post-pandemic eligibility reviews through February 2025, later than all other states and beyond the August–December 2024 period used to calculate expansion group enrollment in our main analysis. However, substituting post-unwinding expansion enrollment data (from June 2025) as the baseline, the estimated number of improper Medicaid expansion enrollees in Oregon actually grows from 482,343 to 508,645. Moreover, Oregon’s program integrity challenges predate the 24-month continuous coverage waiver and COVID-era policies: the state already had the nation’s highest estimated improper expansion enrollment rate (57 percent) in 2019.
Structural Flaws of the ACA, Worsened by COVID-Era Policies, Drove Mass Improper Enrollment
On the ACA exchanges, the temporary COVID-era subsidy boosts made benchmark plans fully subsidized for people reporting income between 100 and 150 percent of FPL from 2021 through 2025. Insurers prefer to have plans fully paid by the government because they do not need to provide value to collect premium payments from enrollees. Brokers also benefit from higher enrollment—and therefore larger commissions—when consumers owe no premium, an incentive that leads to the phantom enrollee problem that Paragon has previously documented. Along with the expanded subsidies, Biden administration policies prioritized enrollment over program integrity, including expanding self-attestation of income, tolerating weak pre-enrollment verification, implementing a year-round special enrollment period for this income group, and encouraging automatic re-enrollment. These measures made improper sign-ups pervasive.
Improper enrollment on the ACA exchanges is generally concentrated in states using the HealthCare.gov platform, due to particularly weak controls on unscrupulous brokers, and is especially severe in states that have not expanded Medicaid.
Similarly bad incentives lead to significant improper Medicaid expansion enrollment. States determine eligibility and administer the program, but the federal government pays at least 90 percent of expansion costs, compared with roughly 57 percent on average for traditional Medicaid enrollees. As we have demonstrated, states receive nearly seven times more funding for $1 of state spending on expansion enrollees relative to traditional enrollees. States actually profit when a person eligible under the traditional criteria instead enrolls in the expansion group, since states are then able to receive the higher federal matching rate.
Recent Reforms Help, but More Work Needed to Improve Core Incentives
Congress and the Trump administration have taken steps to restore program integrity in the exchanges and Medicaid expansion. The most important is that Congress allowed the COVID-era subsidy boosts that drove much of the improper exchange enrollment to expire after 2025. For the administration, enforcement has proved more effective so far than regulatory reforms: CMS ended subsidies for nearly 1.5 million people found ineligible for financial assistance or enrolled without authorization, while its 2025 Marketplace Integrity and Affordability rule was largely undone when a federal court vacated eight of its provisions in June 2026.
The One Big Beautiful Bill also added important Medicaid guardrails. Beginning in 2027, states must conduct eligibility redeterminations every six months for expansion adults rather than once a year. The law also addresses duplicative enrollment, financing schemes, and high eligibility-related error rates. Enforcement of the community engagement requirements—which only apply to Medicaid expansion enrollees—should also help cull improper enrollment.
These reforms have improved program integrity in the ACA’s key programs, but policymakers should go further.
On Medicaid expansion, Congress should end the perverse preferential federal matching rate that favors able-bodied expansion adults over traditional enrollees such as children, pregnant women, the elderly, and people with disabilities. Ending the enhanced 90 percent match would force states to bear a meaningful share of the cost of their own eligibility errors and remove the incentive to misclassify traditional enrollees into the higher-paying expansion group. Federal rules should also require real-time verification of income, residency, and cross-state enrollment before coverage begins and end the automatic, ex parte renewals that keep ineligible people on the rolls.
On the ACA exchanges, lawmakers and regulators should require that applicant income be verified prior to subsidy determination instead of relying on self-attestation, and they should end automatic re-enrollment. Zero-premium plans should be eliminated by requiring a minimum premium for every enrollee, since free coverage invites phantom enrollees. Brokers, insurers, and other repeat bad actors should face real financial consequences for facilitating improper enrollment, and subsidy reconciliation should be tightened so that excess advance payments are recovered from the people who received them.
The combined $65 billion cost shows that improper enrollment is not a trivial administrative error. It is the predictable result of programs that reward enrollment while weakening incentives to verify eligibility. Until policymakers change those incentives, improper enrollment will persist in both the ACA exchanges and Medicaid expansion.